
California and Oregon Advance Universal Healthcare: Federal Support Becomes Key Variable
California and Oregon passed legislation last year setting timelines for developing universal healthcare systems. Supporters say it could save billions of dollars and improve access to care, while opponents worry it could disrupt the existing healthcare system. Both states' plans require federal waivers, but experts believe that amid the federal political stalemate, success depends on the White House's political will.
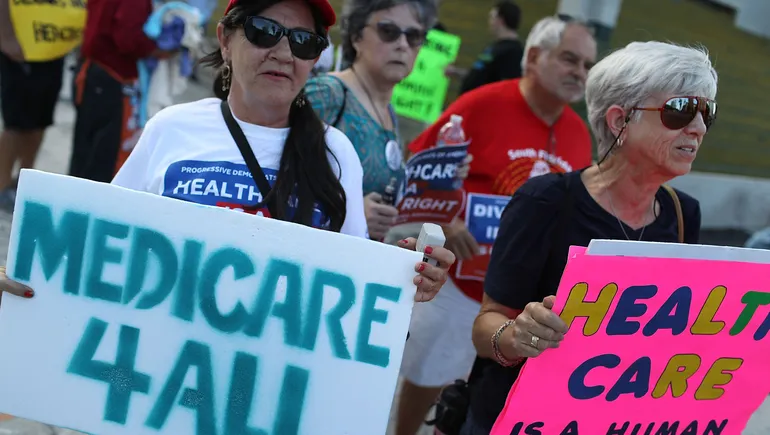
As federal healthcare politics remain deadlocked, California and Oregon are moving closer to achieving universal healthcare coverage. Last year, both state legislatures passed bills setting timelines for establishing publicly funded universal healthcare systems. Supporters argue such systems could save billions in medical costs and improve access to care; opponents warn they could disrupt existing medical services and drive up costs.
Both bills are seen as incremental steps toward a system similar to 'Medicare for All' — a government-run universal health insurance plan popularized by Senator Bernie Sanders during his 2016 and 2020 presidential primary campaigns. Medicare for All is a single-payer model, where the government provides a comprehensive benefits package for everyone and significantly reduces out-of-pocket costs. In contrast, the Affordable Care Act relies on consumers voluntarily purchasing private insurance.
Experts told Healthcare Dive that the success of state-level bills ultimately depends on whether the White House and federal government are willing to approve healthcare reform proposals that go further than current federal policy. The next steps for both states point directly to Washington, where these local policy proposals could reignite the dormant national debate on healthcare coverage.
State bills need federal support
Both bills establish state-level governance frameworks to implement universal coverage, but both require federal approval. Oregon's reform plan is more developed than California's. Oregon Senate Bill 1089 authorizes a nine-member Universal Health Plan Governance Board to develop a plan within two years to implement a single-payer proposal recommended by an earlier Joint Task Force on Universal Health Care. The proposal would eliminate private risk-bearing insurance and provide comprehensive benefits for all residents. Oregon will seek what the federal government calls a 'breakthrough waiver' to allow the state greater flexibility in managing Medicaid and Medicare funds than previous state-level experiments.
California's SB 770 similarly directs the state to negotiate waivers with the federal government to allow the state to merge Medicare, Medicaid, and state funds, but these funds would be used for a vaguely defined 'unified financing' system. Governor Gavin Newsom supported single-payer during his 2018 campaign, but the legislature did not pass it, instead establishing the 'Healthy California for All Commission' in 2019 to make recommendations.
The commission was divided on whether to pay through private insurers and how to pay healthcare providers. In its initial report, commission researchers noted that 'over 60% of Californians with coverage are enrolled in HMOs.' Some commissioners argued that eliminating third-party intermediaries is impractical and makes payment reform impossible; while single-payer supporters argued that allowing private contractors to bear insurance risk would incentivize them to deny necessary medical services, according to the HCFA's final report from April 2022.
Newsom signed SB 770 into law last October. The bill follows the commission's recommendations, calling for a unified financing system to pay for a broad benefits package for all residents while eliminating distinctions between Medicare, Medicaid, the ACA, and employer-sponsored insurance. However, it sidesteps key questions about the structure of major reforms, including whether private insurers will play a role in the future (if any). The bill sets a 2025 deadline for California to develop a 'waiver framework' through informal negotiations with the federal government, allowing the state to consolidate federal insurance programs into a single funding source. But federal waiver applications must include a detailed description of the reform plan, so the Newsom administration must submit a formal waiver application to state legislators in less than two years, addressing the difficult questions SB 770 avoided.
Whether or not private insurers are included, consolidating federal insurance programs into a unified financing system requires federal approval, either through congressional legislation or executive branch waivers of multiple federal laws. Since the ACA, Congress has not chosen to expand healthcare coverage. Soon, California and Oregon may ask the administration to approve unprecedented actions.
States seek cost savings
Supporters of both state bills — including unions, progressive physician groups, and healthcare consumer NGOs — argue that universal coverage is key to solving America's high healthcare costs. According to OECD data, per capita total health spending in the U.S. remains twice the average of other wealthy nations. At the state level, the California Health Care Foundation's 2023 annual survey found that 52% of Californians delayed necessary care due to cost, with 50% of those saying their condition worsened.
The California commission's final report in April 2022 stated that unified financing could fund comprehensive coverage while saving an estimated $517 billion over ten years by controlling hospital, physician, and drug prices, and reducing redundant administrative costs in the current system. This analysis aligns with most single-payer studies, including the Congressional Budget Office's 2020 analysis of a federal option.
California State Senator Scott Wiener said the impact of high healthcare costs on the state's workforce prompted him to draft SB 770. 'I've seen this absurd system where healthcare is tied to employment,' Wiener said. 'If someone is considering changing jobs, they not only think about salary and career advancement, but also worry, 'Will I have health insurance?''
In Oregon, voters like nursery owner Ben Verhoeven hope universal healthcare will lower the high medical costs for his business. Over the past year, Verhoeven paid $196,000 in full premiums for his 26 full-time employees at Peoria Gardens, a family-owned wholesale greenhouse and nursery, but the plan's $2,000 deductible still left employees facing out-of-pocket costs. A few years ago, when Verhoeven's daughter fell from a tree and broke both arms, he received a $2,000 medical bill. 'I care about my employees and want them to be healthy, but I don't want to spend a lot of time studying the healthcare business,' Verhoeven said. 'My job is to grow plants, not to deal with insurance.'
Insurers and hospitals oppose the bills
Major insurers and hospital systems in both states oppose universal coverage. The California Association of Health Plans (representing 47 plans) criticized the state commission for using flawed data to calculate projected cost savings. In comments submitted to the commission, CAHP said the state's cost savings projections rely on assumptions that 'do not reflect reality, or come with serious but understated trade-offs in healthcare access.' If the assumptions are inaccurate, they could 'burden taxpayers with hundreds of billions of dollars.'
Other organizations, including the California Chamber of Commerce and American physician groups, also opposed the bill. These groups joined CAHP in submitting opposition letters to the state Senate Health Committee, stating that a California single-payer system would require over $500 billion in annual public spending and necessitate tax increases. Kaiser Permanente, California's largest health plan and hospital owner, opposes single-payer. In an internal email obtained by Healthcare Dive, Kaiser called it costly, disruptive, and harmful to Kaiser and its members. The email described SB 770 as a 'modest proposal' exploring federal steps toward single-payer, adding, 'While the bill is not ideal, it may help answer important questions about whether the federal government is even willing or able to take the bold actions needed to advance single-payer in California.'
Insurers and health systems (including Kaiser) are also opposing universal coverage in Oregon. In written testimony submitted to the Oregon legislature, state insurers said the single-payer envisioned by SB 1089 'tries to do too much, ignores significant legal and financial challenges, and has no successful precedent in any U.S. state.' The Oregon Hospital Association did not take a position, but the state's two largest hospital owners, Providence Health and Kaiser Permanente (which also operates health plans), signed the testimony. Notably, the American Medical Association chapters in both states neither supported nor opposed the bills. The Oregon Medical Association confirmed its neutral stance on SB 1089. Nationally, the AMA, with 270,000 members, is divided internally on single-payer policy. The California Hospital Association (representing over 400 hospitals) told Healthcare Dive it 'took no position on SB 770.' California's largest nurses' union — a longtime single-payer supporter — opposed SB 770, calling it an unnecessary half-measure. In a letter to Newsom, Carmen Comsti, chief regulatory policy specialist for the California Nurses Association, said the bill is dangerous because it avoids endorsing single-payer, and the vague term 'unified financing' 'could include a multi-payer insurance system, far short of single-payer.'
A narrow path forward
Both California and Oregon hope to implement broad reforms without requiring approval from a gridlocked Congress. Several federal laws allow HHS and the Treasury Department to waive Medicare, Medicaid, and ACA laws to expand coverage, control costs, or improve quality in individual states. For example, Medicaid allows a state to become the sole Medicaid managed care provider in that state, receiving capitated payments. Vermont currently operates such a system. Brown and Peisch, external legal counsel to the California commission, argued in the legal appendix to the final report that this structure could pass federal review for unified financing. However, incorporating Medicare into a state system is legally and administratively more complex than Medicaid. Seniors and disabled adults have federal individual rights to Medicare benefits, and administration does not involve a direct state role. HHS can allow states to develop payment and service models that reduce costs or improve quality.
Brown and Peisch advised the California commission that the best legal path to incorporating Medicare funds into a unified financing or single-payer system is to create an entity that acts as a statewide accountable care organization, a state-exclusive Medicare Advantage provider, or both — similar to the Medicaid structure. But the lawyers warned in a memo that such a move 'would be unprecedented and politically controversial.' Even seemingly innocuous federal rules can become obstacles, according to Anthony Wright, a HCFA commissioner and executive director of Health Access, a California NGO. Although waiver rules for ACA subsidy funds are the most flexible, if a proposal merely enrolls more eligible people in ACA coverage, the state could violate budget neutrality rules. 'Even relatively small reforms are blocked' because states are unwilling to waste time applying, Wright said, and unified financing faces many similar obstacles.
Adding to the complexity, the Employee Retirement Income Security Act (ERISA), the federal law governing employer-sponsored insurance, contains preemption clauses that bar states from nearly all regulation of self-insured health plans. Elizabeth McCuskey, a professor at Boston University, and Erin Fuse Brown, a professor at Georgia State College of Law, reviewed ERISA's impact on 66 state single-payer proposals in 2020 for the University of Pennsylvania Law Review, concluding that ERISA is a 'trap' that 'threatens to obstruct state transformative experiments.' But Oregon's plan may still have hope. As consultants to the Oregon task force, McCuskey and Fuse Brown found the state's proposal 'could withstand an ERISA challenge.' The proposal relies on economic incentives to encourage employers to have workers receive benefits from the state, rather than directly prohibiting them. However, an unconstrained multi-payer approach sacrifices potential administrative savings, so the lawyers recommended allowing employers to make payments to the state for workers, or vice versa.
Depends on political will
According to the California commission's final report, achieving state goals without Congress 'will depend largely on the current federal administration's interest in supporting state-level unified financing systems.' The two leading candidates in the 2024 presidential election — President Joe Biden and former President Donald Trump — have both expressed concerns about single-payer healthcare. Seema Verma, the Trump administration's healthcare policy chief and CMS administrator, expressed skepticism about universal reform during a Q&A after a 2018 Commonwealth Club speech. 'I think many analyses show it's unaffordable,' Verma said. 'There's no point wasting time trying something that won't work.' Biden also voiced financial concerns about federal Medicare for All during the 2020 primary, asking supporters how to 'find the money.'
These questions will continue to simmer for the rest of the year. California HHS has 11 months to gather stakeholder input, address unresolved issues from SB 770, and prepare to open negotiations with the White House in January 2025. In Oregon, policymakers are optimistic that state-level universal coverage could soon become a reality. Bruce Goldberg, who chaired the Oregon task force and was recently appointed by Governor Tina Kotek to the new Universal Health Plan Governance Board, hopes the state can become the first to provide comprehensive insurance for all with federal support. 'You can read all the regulations. Ultimately, there's a regulatory path, so what really matters is political will,' Goldberg said. 'That's why I think it's important to have a strong, broad grassroots coalition, not just a group of policy experts. We all know we have a complex and unjust system.'